



body{font-family:system-ui,-apple-system,Segoe UI,Roboto,Ubuntu,Cantarell,Noto Sans,sans-serif;line-height:1.6;margin:0;padding:32px;background:#fff;color:#111} h1,h2{color:#0f172a;margin-bottom:.4em} h1{font-size:clamp(1.6rem,2.2vw,2.2rem)} h2{font-size:clamp(1.2rem,1.9vw,1.6rem);margin-top:1.4em} h3{margin:.9em 0 .3em} ul,ol{margin:.5em 0 .9em 1.2em} table{width:100%;border-collapse:collapse;margin:1em 0;background:#fff;border:1px solid #e5e7eb} th,td{padding:10px 12px;border-bottom:1px solid #e5e7eb;vertical-align:top} th{background:#eef6ff;text-align:left} .card{background:#f8fafc;border:1px solid #e5e7eb;border-radius:12px;padding:14px;margin:.8em 0} .tiny{font-size:.9rem;color:#475569} footer{margin-top:24px;font-size:.9rem;color:#475569}
Plantar fasciitis is a common clinical label for pain arising near the plantar fascia’s attachment at the medial heel. Patients typically report pain with their first steps after getting out of bed or standing after prolonged rest. Symptoms may ease temporarily with movement and then increase after extended standing, walking, running, or other loaded activity.
Iontophoresis uses controlled direct current to assist the movement of an appropriately charged medication through intact skin. In a plantar-fasciitis treatment plan, the medication electrode is usually positioned near the point of greatest tenderness at the plantar-fascia origin.
Iontophoresis should be described accurately as a possible short-term adjunct, not as the foundation of plantar fasciitis rehabilitation.
The 2023 Clinical Practice Guideline for heel pain recommends manual therapy, stretching, and combined orthotic treatment in preference to electrotherapeutic modalities for short- and long-term improvement. Iontophoresis may be considered a second-line intervention when clinically appropriate.
Clinical scope: This guide provides an evaluation and treatment-planning framework for licensed healthcare professionals. It does not prescribe a medication, concentration, polarity, dose, current, treatment frequency, or total number of applications.
For general medication, polarity, electrode-filling, and controller instructions, use our Iontophoresis Electrode Directions for Use rather than duplicating those instructions here.
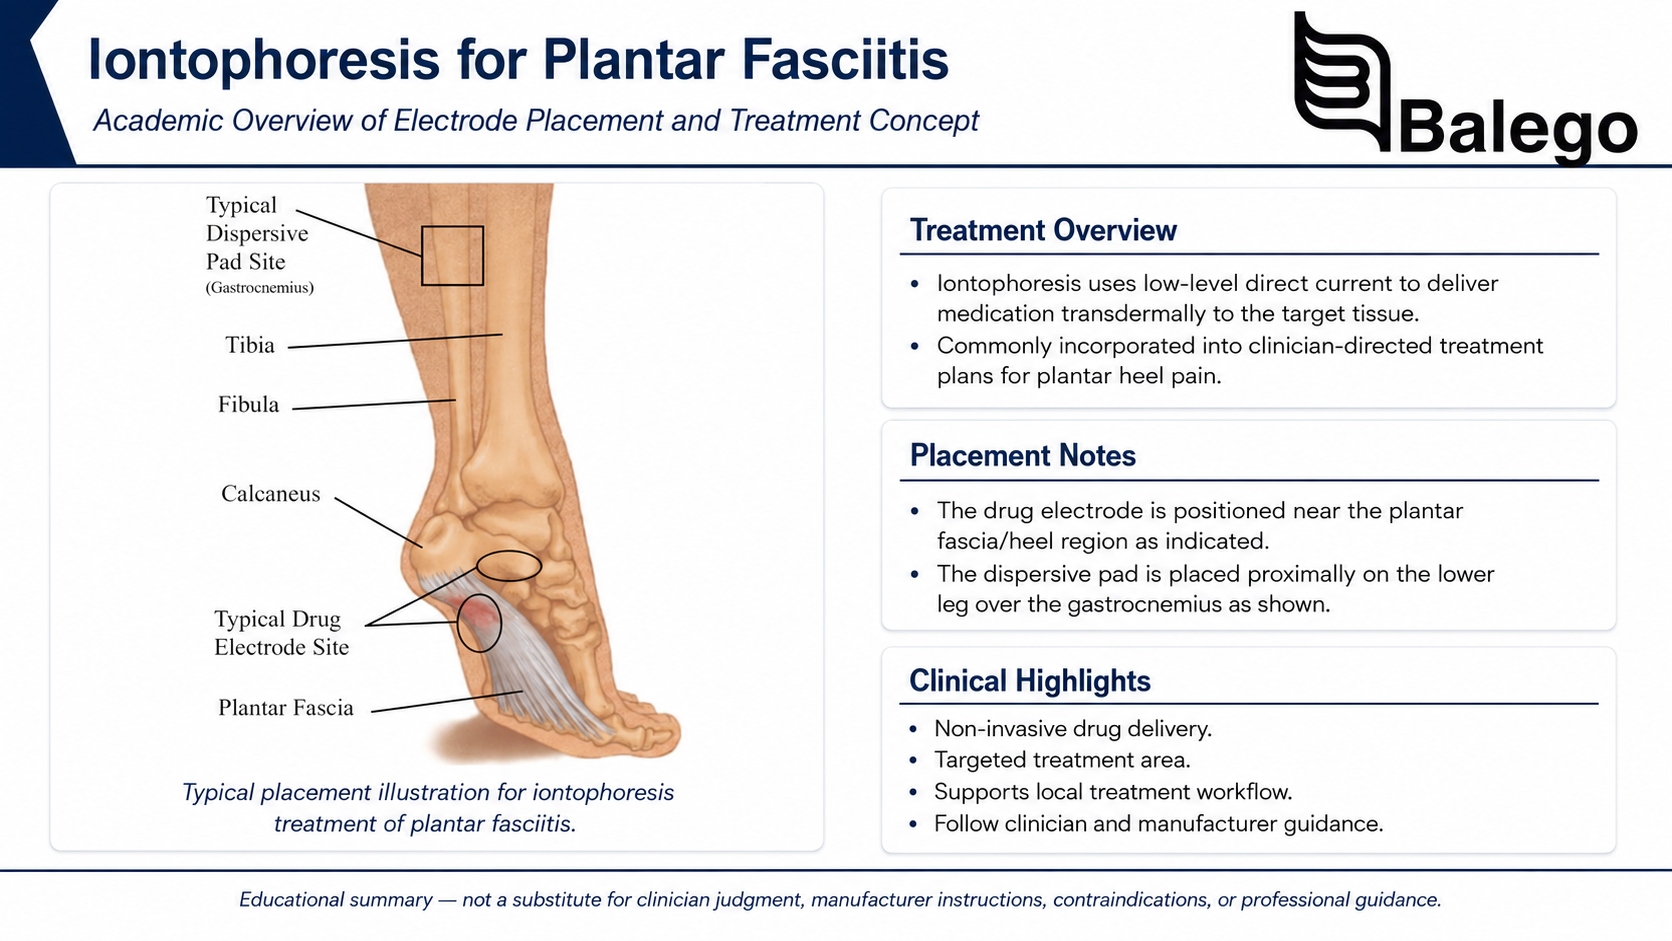
Plantar Fasciitis Iontophoresis: Quick Clinical Summary
| Clinical question | Practical answer |
|---|---|
| Where is plantar-fasciitis pain usually located? | Near the plantar-medial heel, frequently at the medial calcaneal tubercle |
| What symptom pattern is characteristic? | First-step pain after sleep or prolonged rest, followed by pain after sustained loading |
| Is imaging routinely required? | No, diagnosis is usually clinical unless the presentation is atypical or another condition is suspected |
| Where is the medication electrode placed? | Over or immediately adjacent to the point of maximum tenderness at the plantar-fascia origin |
| Can the electrode always be placed directly beneath the heel? | No; callus, weight-bearing, footwear pressure, skin condition, and electrode fit may require an adjacent medial placement |
| Where is the return electrode placed? | On intact proximal soft tissue according to the selected electrode and controller instructions |
| Is iontophoresis first-line treatment? | No, current guidelines position it as a possible second-line treatment |
| What should accompany iontophoresis? | Load modification, plantar-fascia and calf stretching, progressive strengthening, appropriate taping or footwear support, and measurable reassessment |
| What should determine medication and polarity? | The prescriber’s order, exact medication formulation, pharmacist confirmation, and product instructions |
| When should treatment be reconsidered? | When the diagnosis is uncertain, symptoms worsen, skin irritation develops, or no measurable benefit occurs, |
What Is Plantar Fasciitis?
The plantar fascia is a thick connective-tissue structure extending from the heel toward the toes. It supports the longitudinal arch and helps transmit force as the foot accepts and releases body weight.
Symptoms most commonly arise close to its attachment at the medial calcaneal tubercle. Although the familiar name is “plantar fasciitis,” persistent presentations can involve a mixture of irritation, collagen disorganization, and degenerative tissue changes rather than a purely inflammatory process. Iontophoresis should therefore not be presented as repairing or regenerating the fascia.
Typical clinical presentation
Common findings include:
- Gradual onset of plantar-medial heel pain
- Pain with the first steps in the morning
- Pain after sitting or resting
- Tenderness immediately in front of the heel bone
- Pain after prolonged standing or walking
- Symptoms after, rather than necessarily during, exercise
- Limited ankle dorsiflexion
- Tightness in the gastrocnemius or soleus
- Reduced tolerance for barefoot walking on hard floors
- Pain during push-off or repeated loading
AAOS identifies first-step pain, plantar heel tenderness, limited ankle dorsiflexion, increased activity, prolonged standing, calf tightness, high or low arches, and increased mechanical loading among the common findings and associated factors.
A heel spur is not the diagnosis
A calcaneal spur may appear on an X-ray, but many people with heel spurs have no heel pain. The presence or size of a spur alone does not confirm plantar fasciitis or justify iontophoresis.
Where Does Iontophoresis Fit in Plantar-Fasciitis Care?
Iontophoresis is best positioned as one element of a comprehensive plan rather than a stand-alone treatment.
Current guideline position
The 2023 heel-pain guideline gives electrotherapy a lower recommendation grade than several active and mechanical interventions. It states that clinicians may use iontophoresis as a second-line treatment, while recommending manual therapy, stretching, taping, night splints for persistent first-step pain, and orthoses combined with other treatments.
A clinically defensible order of care is, therefore, the following:
- Confirm that the symptom pattern fits plantar fasciitis.
- Identify mechanical and loading contributors.
- Begin education, stretching, manual therapy, taping, footwear modification, and progressive exercise.
- Add iontophoresis when short-term symptom reduction could help participation in that active program.
- Reassess objective outcomes after a defined trial.
- Escalate or refer when progress is insufficient.
Iontophoresis may be considered when:
- Pain is localized near the superficial plantar-fascia origin.
- The diagnosis is reasonably clear.
- The skin is intact.
- A prescriber has selected a suitable ionized medication.
- Medication polarity is verified.
- The patient is an appropriate candidate for direct-current treatment.
- Pain is limiting participation in stretching, strengthening, walking, or work.
- First-line rehabilitation is already underway.
- Short-term symptom control has a defined functional purpose.
- Progress will be measured rather than assumed.
What Does the Research Show?
Direct plantar-fasciitis iontophoresis research is limited and mainly addresses short-term results.
Evidence summary
| Evidence | Treatment examined | Main interpretation |
|---|---|---|
| 1997 randomized controlled trial | Traditional modalities with either placebo or 0.4% dexamethasone iontophoresis | Dexamethasone produced more immediate improvement, but the advantage was not maintained clearly at one month |
| 2006 randomized controlled trial | Six iontophoresis treatments combined with continuous LowDye taping and calf stretching | Some short-term symptom differences were observed, but iontophoresis was part of a bundled program |
| 2023 clinical practice guideline | Review of physical-therapy interventions for plantar heel pain | Iontophoresis may be used as second-line care; manual therapy, stretching, and combined orthotic care are preferred |
| Current clinical interpretation | Iontophoresis added to rehabilitation | It may support short-term symptom modification but should not replace active care |
The 1997 study included 40 affected feet and compared traditional treatment plus placebo iontophoresis with traditional treatment plus dexamethasone iontophoresis. Both groups received six treatments over two weeks. The published findings have generally been interpreted as supporting short-term improvement rather than a durable superiority at later follow-up.
The 2006 trial involved 31 participants with medial-calcaneal-origin plantar fasciitis. Every participant received six iontophoresis sessions over two weeks, continuous LowDye taping, and gastrocnemius-soleus stretching. Participants received dexamethasone, acetic acid, or placebo solution. The iontophoresis dose was 40 mA·min with the current adjusted up to 4 mA according to tolerance. Because every group also received taping and stretching, the results do not establish iontophoresis as an effective stand-alone treatment.
How to use the historical research responsibly
The six-treatment, two-week, 40 mA·min regimen is a published research protocol, not a universal prescription.
A current treatment plan must still consider the following:
- Prescriber instructions
- Medication labeling
- Medication concentration and formulation
- Electrode maximum dose
- Controller limits
- Patch design
- Skin tolerance
- Clinical response
- Facility policy
- Applicable scope-of-practice rules
Confirm the Diagnosis Before Treating
“Plantar heel pain” is a symptom region, not a diagnosis.
The 2023 guideline emphasizes that plantar heel pain can represent several different conditions and recommends additional diagnostic assessment when the presentation does not match plantar fasciitis or when symptoms fail to resolve as expected.
History questions
Document:
| Question | Clinical significance |
|---|---|
| Where is the pain most intense? | Plantar fasciitis is usually concentrated near the plantar-medial heel |
| Is pain worse with the first morning steps? | Supports the typical plantar-fasciitis pattern |
| Does it improve briefly after walking? | Common characteristic |
| Is pain greater during or after activity? | Helps distinguish loading behavior |
| Was there an acute injury? | Raises concern for fascia tear, fracture, or other trauma |
| Has activity volume changed recently? | Running, walking, work, or training changes may have increased load |
| How much time is spent standing? | Prolonged standing can contribute to symptoms |
| What footwear is used? | Worn, minimally supportive, or recently changed footwear may influence loading |
| Is there numbness, tingling, or burning? | Suggests possible nerve involvement |
| Is pain present at night or at rest? | May indicate an atypical presentation requiring further evaluation |
| Is pain bilateral? | May warrant screening for systemic or inflammatory contributors |
| Is there diabetes or impaired sensation? | Changes skin, circulation, and treatment-risk considerations |
| What treatment has been attempted? | Identifies failed strategies and prevents unnecessary repetition |
| What medications and allergies are present? | Essential before medication delivery |
Physical examination
Observation
Assess:
- Gait
- Willingness to load the heel
- Arch posture
- Footwear wear pattern
- Swelling or bruising
- Skin integrity
- Callus
- Color and temperature
- Foot and ankle alignment
- Ability to perform a controlled heel raise
Palpation
Palpate:
- Medial calcaneal tubercle
- Proximal plantar fascia
- Central heel pad
- Calcaneal body
- Achilles insertion
- Tarsal-tunnel region
- Abductor hallucis region
- Any palpable plantar nodules
Maximum tenderness just anterior to the plantar heel supports plantar fasciitis. Diffuse central heel-pad pain, focal calcaneal-body pain, posterior heel pain, or neurologic symptoms may indicate a different condition.
Mobility
Measure:
- Weight-bearing ankle dorsiflexion
- Non-weight-bearing dorsiflexion
- Gastrocnemius flexibility
- Soleus flexibility
- Great-toe extension
- Plantar-fascia tension during toe extension
- Midfoot and rearfoot mobility when clinically relevant
Provocation
Useful findings can include:
- Pain with palpation at the medial calcaneal tubercle
- Pain reproduced with the windlass test
- Pain during the first steps after rest
- Symptoms during prolonged loading
- Restricted ankle dorsiflexion
The guideline identifies medial calcaneal-tubercle palpation, weight-bearing and non-weight-bearing windlass testing, stress-fracture screening, heel-pad assessment, and neurologic provocation as useful parts of the examination.
Strength and load tolerance
Assess according to irritability:
- Single-leg heel-raise tolerance
- Calf strength
- Intrinsic-foot control
- Toe-flexor function
- Posterior-tibial function
- Walking tolerance
- Stair tolerance
- Running or sport-specific loading
Do not provoke repeated high-intensity pain simply to produce a baseline number.
Conditions That Can Resemble Plantar Fasciitis
| Possible diagnosis | Findings that may distinguish it |
|---|---|
| Calcaneal stress fracture | Focal bone pain, pain with calcaneal compression, rapid training increase, or persistent weight-bearing pain |
| Heel-pad syndrome or atrophy | More central heel pain with a bruised feeling, often aggravated by hard surfaces |
| Baxter nerve entrapment | Burning, radiating, or neurological medial heel symptoms |
| Tarsal tunnel syndrome | Numbness, tingling, burning, or positive nerve provocation |
| Plantar fibromatosis | Palpable nodule within the plantar fascia |
| Plantar-fascia tear | Sudden pain, bruising, swelling, or traumatic onset |
| Achilles insertional disorder | Posterior rather than plantar heel pain |
| Fat-pad contusion | Direct-impact history and central heel tenderness |
| Inflammatory arthropathy | Bilateral heel pain, prolonged stiffness, or systemic symptoms |
| Referred lumbar pain | Neurologic signs or symptoms extending beyond the foot |
| Infection or wound-related pain | Redness, heat, drainage, fever, or skin breakdown |
Imaging is not routinely required for a classic presentation. X-ray, ultrasound, or MRI may be considered when trauma, stress fracture, fascia rupture, mass, arthritis, or another source of heel pain is suspected.
Red Flags and Referral Criteria
Obtain medical evaluation before proceeding when there is
- Acute trauma with inability to bear weight
- Marked bruising or swelling
- Suspected calcaneal stress fracture
- Sudden tearing or popping at the plantar heel
- Open skin, ulceration, or infection
- Fever or systemic illness
- Progressive numbness or weakness
- Significant loss of protective sensation
- Severe night or resting pain
- A palpable enlarging mass
- Bilateral heel pain with inflammatory symptoms
- Persistent symptoms that do not respond to a properly followed plan
- Uncertainty about medication, formulation, or polarity
- An implanted electronic device or medical condition listed as a contraindication by the iontophoresis product
Selecting the Treatment Target
Usual target
The medication electrode is generally centered over the most localized tenderness at the proximal plantar fascia, commonly near the medial calcaneal tubercle.
A visible diagram should identify:
- The medial calcaneal tubercle
- The proximal central band of the plantar fascia
- The location of maximum tenderness
- A possible medial-heel electrode position
- A possible plantar position when skin and product fit allow
- The proximal return-electrode location
Plantar placement vs. medial placement
| Placement | Possible advantage | Possible limitation |
|---|---|---|
| Direct plantar placement | Positions the medication reservoir over the most tender region | Thick callus, weight-bearing, sweating, shoe pressure, and walking can interfere with contact |
| Medial heel placement | May reduce direct pressure during standing and fit the foot contour more effectively | Must remain close enough to the clinically selected target |
| Proximal arch placement | May fit some elongated pain patterns | Should not replace accurate localization of the primary lesion |
| Wearable patch spanning the heel | Allows out-of-clinic delivery | Shape and reservoir location must remain stable during walking |
| Small controller-based electrode | Allows precise targeting and direct current control | Requires the patient to remain connected during treatment |
The best site is not always the exact point where the patient steps. Electrode contact, skin quality, current density, and anatomical fit are essential safety considerations.
Skin Preparation: Follow the Selected Product
Some controller-based electrode kits include alcohol preparation pads. In contrast, IontoPatch instructs users to clean with soap and water, dry thoroughly, and avoid an alcohol wipe because it may dry and irritate the skin.
Product-specific preparation rule
| Product format | Preparation approach |
|---|---|
| IontoPatch wearable patch | Follow IontoPatch instructions, including soap-and-water preparation |
| ACTIVApatch | Follow the instructions supplied with the selected ACTIVApatch model |
| Trivarion or Ionto4 electrode | Follow the electrode kit and controller instructions |
| Buffered Balego iontophoresis kit | Follow the kit instructions and facility protocol |
| Another brand or electrode system | Use only that manufacturer’s directions |
General principles include:
- Use intact skin.
- Remove lotion, oil, and heavy contamination.
- Dry the skin completely.
- Clip excessive hair when necessary.
- Do not shave immediately before treatment.
- Avoid fissures, blisters, callused cracks, wounds, and irritated skin.
- Inspect both medication and return sites.
- Do not improvise skin-prep products.
Plantar Fasciitis Iontophoresis Protocol Framework
Step 1: Confirm the medical order
Verify:
- Exact medication name
- Exact chemical formulation
- Concentration
- Volume
- Ionic charge
- Required electrode polarity
- Prescribed mA·min dose
- Maximum current
- Treatment frequency
- Intended treatment series
- Medication allergy history
- Treatment location
Do not infer polarity from a medication’s general drug class or brand name. Use the precise formulation ordered by the prescriber.
Step 2: Record baseline outcomes
At minimum, document:
- First-step pain on a 0–10 scale
- Pain after a defined period of walking or standing
- Palpation tenderness
- Weight-bearing dorsiflexion
- Functional score
- Walking tolerance
- Work or sport limitation
- Skin condition
Suitable functional measures include:
- Foot and Ankle Ability Measure
- Foot Function Index
- Lower Extremity Functional Scale
- Patient-Specific Functional Scale
- Numerical Pain Rating Scale
The heel-pain guideline emphasizes the use of validated function and outcome measures rather than relying solely on palpation or a general report that the heel “feels better."
Step 3: Mark the medication site
Before preparing the electrode:
- Palpate the plantar-fascia origin.
- Identify the smallest reproducible region of maximum tenderness.
- Note callus, skin folds, fissures, or pressure sensitivity.
- Decide whether plantar or medial placement provides safer full contact.
- Mark the selected location.
Step 4: Select an electrode or patch
Consider:
- Target footprint
- Medication volume
- Prescribed dose
- Skin sensitivity
- Plantar callus
- Heel curvature
- Patient weight-bearing demands
- Shoe or brace use
- Need for current monitoring
- Clinic scheduling
- Patient ability to follow removal instructions
Step 5: Prepare the skin and electrodes.
Follow the exact instructions for the selected product.
Do not:
- Overfill the reservoir
- Place medication on the adhesive
- Reuse a single-use electrode
- Place an electrode over broken skin
- Cut an electrode unless specifically permitted
- Substitute a TENS pad for an iontophoresis electrode
- Use a preparation method from a different manufacturer
Step 6: Position the medication electrode
Place the active reservoir.
- Over or adjacent to the marked plantar-fascia origin
- With the entire conductive surface in contact
- Away from cracked callus or skin breakdown
- Without wrinkles or lifted edges
- Without concentrated pressure from footwear
- According to the prescribed medication polarity
Step 7: Position the return electrode
Place the return electrode:
- On intact proximal soft tissue
- Where it can remain fully adhered
- Away from prominent bone
- At the distance specified by the product instructions
- Without crossing the chest or another contraindicated current path
- According to the controller and electrode labeling
The calf is one possible location, but it should not be presented as mandatory for every product or patient.
Step 8: Deliver the prescribed dose
Controller-based treatment
With the ActivaDose II Iontophoresis Controller, the practitioner selects the dose and current while the device calculates treatment time. The controller provides adjustable dosing from 0–80 mA·min, current up to 4 mA, automatic ramping, circuit monitoring, and treatment alerts.
During treatment:
- Keep the foot supported.
- Minimize electrode movement.
- Monitor comfort and skin sensation.
- Watch the controller’s resistance and electrode indicators.
- Reduce or stop current for burning or sharp pain.
- Do not continue through a repeated electrode-reject alarm.
Wearable treatment
With a wearable patch:
- Confirm the correct chamber or reservoir.
- Apply the precise ordered medication volume.
- Complete any required return-chamber preparation.
- Secure the full adhesive border.
- Record the application time.
- Give the patient the planned removal time.
- Explain how to respond to lifting, burning, or moisture exposure.
- Avoid footwear or braces that compress the reservoirs.
- Do not extend wear beyond the product instructions.
Step 9: Inspect the skin
After controller treatment or patch removal:
- Inspect both treatment sites.
- Record the location and extent of redness.
- Ask about burning or itching.
- Look for blistering or skin breakdown.
- Document adhesive reactions.
- Delay further treatment over irritated skin.
- Report a suspected medication reaction.
Step 10: Reassess the functional purpose
Ask whether short-term symptom reduction produced a meaningful gain:
- Were the first morning steps easier?
- Could the patient walk farther?
- Was calf or plantar-fascia stretching better tolerated?
- Did work-standing tolerance improve?
- Could strengthening progress?
- Was pain after activity reduced?
- Did the patient reduce compensatory gait?
A change in tenderness alone is insufficient when walking and function remain unchanged.
Historical Research Protocol vs. Current Clinical Plan
| Element | 2006 research protocol | Current clinical interpretation |
|---|---|---|
| Participants | Medial-calcaneal-origin plantar fasciitis | Confirm a comparable diagnosis before applying the results |
| Treatments | Six sessions over two weeks | A possible reference point, not a mandatory schedule |
| Electrical dose | 40 mA·min | Must still follow the current order and product limits |
| Current | Up to 4 mA based on tolerance | Current should follow controller, electrode, and patient requirements |
| Medication groups | Dexamethasone, acetic acid, or placebo | Medication must be selected by the current prescriber |
| Additional care | Continuous LowDye taping and calf stretching | Results cannot be attributed solely to iontophoresis |
| Outcome | Short-term pain and stiffness | Long-term load tolerance and function still require rehabilitation |
Comparing Balego Iontophoresis Options for Heel Treatment
This comparison focuses on heel-specific workflow rather than repeating the complete specifications available on each product page.
| Balego product | Format | Heel-related advantage | Important consideration |
|---|---|---|---|
| ActivaDose II Controller | Reusable wired controller | Direct control of current, dose, treatment time, and skin response | Requires a compatible disposable electrode kit |
| Trivarion Delivery Kits | Flexible controller-based electrodes | A form-fitting design and several reservoir sizes can help on curved anatomy | The selected shape must still fit the medial or plantar heel safely |
| Ionto4 Electrode Kits | Controller-based square or butterfly electrodes | Four shape and fill-volume options support site-specific selection | Larger footprints may not suit every heel or arch |
| Balego Buffered Iontophoresis Electrode Kits | Controller-based drug and return electrodes | Buffered return electrode and four size choices | Skin preparation and placement must follow the kit instructions |
| IontoPatch | Self-contained wearable patch | No external controller; 4-, 8-, and 14-hour average wear-time options | Pressure, sweating, walking, and heel callus may affect placement |
| ACTIVApatch | Self-contained wearable patch | No wires or saline; treatment windows from about 1.25 to 12 hours | Patch shape and footwear interaction must be evaluated |
Product-specific details
The Trivarion electrode family includes small, medium, butterfly, and large options from 1.5 to 3.5 cc. Its flexible design is intended to conform to curved and uneven treatment areas.
The Ionto4 family offers small, medium, large, and butterfly electrodes with 1.5–4.0 cc fill volumes.
IontoPatch is available as STAT, 80, and Extra Strength. The models provide 80 or 120 mA·min over average wear periods of approximately 4, 8, or 14 hours. Medication is supplied separately.
ACTIVApatch includes IntelliDose 2.5, IontoGo 4.0, and IontoGo 12.0. These non-saline wearable products provide 40- or 80-mA·min options over average treatment periods from approximately 1.25 to 12 hours.
Controller-based treatment may be preferable when:
- This is the first iontophoresis treatment.
- Skin response requires direct observation.
- The treatment target is small.
- Exact current control is important.
- A flexible electrode can fit the medial heel better than a patch.
- The patient has difficulty following extended-wear instructions.
- Walking or footwear would displace a wearable patch.
A wearable patch may be preferable when:
- The clinician has established medication and placement.
- The patch maintains full contact on the selected area.
- The patient needs to leave the clinic.
- Lower-current delivery over a longer interval is preferred.
- A shoe, brace, or job will not compress the patch.
- The patient understands skin monitoring and removal.
Iontophoresis Compared with Other Plantar-Fasciitis Treatments
| Treatment | Main purpose | Guideline position | Principal limitation |
|---|---|---|---|
| Education and load modification | Reduces repeated aggravating load | Foundational | Requires behavior and activity change |
| Plantar-fascia stretching | Improves tissue mobility and first-step tolerance | Strongly supported | Requires regular adherence |
| Calf stretching | Addresses limited dorsiflexion and calf restriction | Strongly supported | Must be performed consistently |
| Manual therapy | Addresses relevant joint and soft-tissue restrictions | Strongly supported | Requires individualized examination |
| Taping | Short-term pain reduction and load modification | Recommended for short-term use | Skin tolerance and effect duration vary |
| Orthoses | Helps redistribute load when combined with other treatments | Useful as part of combined care | Not recommended as isolated short-term treatment |
| Night splint | Maintains length overnight | Recommended for persistent first-step pain | Comfort and adherence can be difficult |
| Progressive strengthening | Improves foot and calf capacity | Important part of active rehabilitation | The load must be progressed gradually |
| Iontophoresis | Localized medication delivery | Possible second-line treatment | Primarily short-term evidence |
| Low-level laser | Short-term pain reduction within rehabilitation | Supported by the 2023 guideline | Should not replace active rehabilitation |
| Therapeutic ultrasound | Historically used physical agent | Not recommended to add to stretching | Limited evidence of additional benefit |
| Corticosteroid injection | Short-term anti-inflammatory procedure | Used for persistent symptoms | Repeated injection may weaken the fascia |
| Shockwave therapy | Noninvasive option for persistent cases | Used selectively | Results and access vary |
| Surgery | Treatment for severe refractory cases | Reserved for prolonged failed conservative care | Operative risk and recovery |
The 2023 guideline supports manual therapy, stretching, taping, combined orthotic treatment, night splints for persistent morning pain, and short-term laser therapy. It advises against using therapeutic ultrasound to enhance stretching outcomes and classifies iontophoresis as second-line.
AAOS reports that most patients improve with nonsurgical care and reserves surgery for prolonged symptoms that fail an appropriate conservative program. It also notes that corticosteroid injections can weaken the plantar fascia and may increase rupture risk, particularly when repeated.
Rehabilitation That Should Accompany Iontophoresis
1. Load management
Temporarily reduce or modify activities that repeatedly provoke symptoms, such as:
- Running volume
- Hill training
- Jumping
- Prolonged standing
- Barefoot walking on hard floors
- Sudden increases in step count
- Worn or minimally supportive footwear
Complete inactivity is rarely the long-term goal. The objective is to bring load within the tissue’s current capacity and then rebuild that capacity.
2. Plantar-fascia stretching
The plantar-fascia-specific stretch is commonly performed by extending the toes while palpating tension through the fascia.
It is particularly useful:
- Before the first morning steps
- After prolonged sitting
- Before standing after rest
- As part of a clinician-designed mobility program
3. Gastrocnemius and soleus stretching
Both straight-knee and bent-knee calf stretching may be needed because the gastrocnemius and soleus contribute differently to ankle dorsiflexion.
4. Progressive strengthening
Depending on irritability, progression may include the following:
- Isometric calf loading
- Double-leg heel raises
- Single-leg heel raises
- A bent-knee soleus raises
- Intrinsic-foot exercise
- Toe-flexor exercise
- Progressive loaded plantar-flexion exercise
- Gradual return to running or work demands
Our exercise resistance bands can support clinician-directed ankle and foot strengthening when external resistance is appropriate.
5. Taping and footwear support
Taping may provide short-term symptom reduction and can help determine whether temporary load redistribution improves walking.
Foot orthoses should generally be combined with stretching, exercise, and other care rather than used as the only intervention.
Our heel lifts and inserts may be appropriate for selected biomechanical or footwear needs, but an adjustable heel lift is not automatically a plantar-fasciitis orthosis and should not be prescribed without considering the full lower-extremity mechanics.
6. Cold therapy
Cold may provide short-term comfort after activity. We offer reusable hot and cold therapy products.
Do not place an excessively cold pack directly on the skin, and do not combine heat or cold with an attached iontophoresis patch unless the product instructions specifically permit it.
Reassessment and Stopping Rules
A defined treatment trial should answer whether iontophoresis is adding meaningful value.
Recommended outcome table
| Outcome | Baseline measure | Reassessment |
|---|---|---|
| First-step pain | 0–10 pain rating | Same question and conditions |
| Walking tolerance | Minutes, distance, or steps | Repeat the same activity |
| Standing tolerance | Time before pain limits function | Repeat under comparable conditions |
| Palpation tenderness | Standardized location and pressure | Same examiner and location |
| Ankle dorsiflexion | Weight-bearing lunge or goniometric measure | Same method |
| Heel-raise capacity | Repetitions or load | Same technique |
| Function | FAAM, FFI, LEFS, or PSFS | Repeat the same instrument |
| Morning stiffness | Duration | Compare daily patterns. |
| Skin response | Redness, irritation, blistering | Inspect after every treatment |
| Medication tolerance | Local or systemic reaction | Review after every treatment |
Continue when:
- Skin remains suitable.
- First-step pain is decreasing.
- Walking or standing tolerance improves.
- The patient is progressing with exercise.
- The treatment helps active rehabilitation.
- The medication remains appropriate.
- Improvement is measurable and clinically meaningful.
Modify or discontinue when:
- Burning, blistering, or persistent irritation occurs.
- The patch repeatedly fails to adhere.
- Medication or saline leaks.
- Pain worsens.
- Neurologic symptoms develop.
- No functional improvement occurs.
- Only temporary tenderness reduction occurs without improved loading.
- Treatment interferes with walking, footwear, or exercise.
- The diagnosis becomes uncertain.
- Repeated treatments are being given without a defined goal.
Suggested Documentation Template
Evaluation
- Affected foot:
- Symptom duration:
- Exact pain location:
- First-step pain:
- Walking tolerance:
- Standing tolerance:
- Running or work demands:
- Medial calcaneal-tubercle tenderness:
- Windlass response:
- Weight-bearing dorsiflexion:
- Gastrocnemius flexibility:
- Soleus flexibility:
- Heel-raise capacity:
- Neurologic screening:
- Differential diagnoses considered:
- Skin condition:
- Relevant medical history:
- Previous treatment:
Iontophoresis order
- Medication:
- Exact formulation:
- Concentration:
- Prescriber:
- Volume:
- Polarity:
- Electrical dose:
- Maximum current:
- Treatment frequency:
- Planned number of applications:
- Device or patch:
- Electrode size:
- Medication-electrode location:
- Return-electrode location:
Treatment response
- Current achieved:
- Treatment duration:
- Patient sensation:
- Device or electrode alerts:
- Skin before treatment:
- Skin after treatment:
- First-step pain change:
- Walking or standing change:
- Exercise progression:
- Continue, modify, discontinue, or refer:
Frequently Asked Questions
Is iontophoresis effective for plantar fasciitis?
Evidence suggests that iontophoresis may provide short-term symptom relief when used with other treatments. Current guidelines classify it as a possible second-line intervention rather than preferred first-line care.
Is iontophoresis better than stretching?
No. Stretching is a core guideline-supported intervention. Iontophoresis may be added when short-term symptom relief is needed to support active rehabilitation.
Is iontophoresis better than a corticosteroid injection?
There is not enough direct evidence to claim that iontophoresis is clinically equivalent or superior to injection. The two treatments deliver medication through different methods and have different risks, indications, and evidence.
Which medication is used?
Only the medication ordered by the prescriber. The exact formulation, concentration, charge, volume, and polarity must be confirmed before treatment.
Is dexamethasone always placed on the negative electrode?
Dexamethasone sodium phosphate is commonly negatively charged, but the exact medication formulation must be verified rather than assumed. Medication polarity should be confirmed by the prescriber or pharmacist.
Can acetic acid be used?
Acetic-acid iontophoresis has been studied in plantar-fasciitis research. That does not make it an interchangeable substitute for a prescribed corticosteroid or saline solution. The prescriber must select the medication and formulation.
Is 40 mA·min the standard dose?
A 40 mA·min dose was used in published studies and is a common controller-based dose. It is not mandatory for every patient. Follow the order and the selected electrode’s maximum dose.
How many treatments are needed?
Several historical studies used six treatments over two weeks, but there is no universal treatment count. Define a reassessment point and discontinue treatment when there is no measurable benefit.
Should the electrode be placed directly on the sole?
It may be placed at the plantar point of maximum tenderness when the skin and electrode fit permit. Medial placement may be preferable when direct weight-bearing, thick callus, sweating, or footwear would disrupt contact.
Where is the return electrode placed?
It is placed proximally on intact soft tissue according to the selected electrode and controller instructions. The calf is common but is not the only permissible location.
Can a wearable iontophoresis patch be used on the heel?
Yes, when the patch can maintain full contact and is not compressed or displaced by walking or footwear. A controller-based flexible electrode may fit some heels better.
Can the patient walk while wearing a patch?
Wearable products are designed to permit mobility, but walking must not displace, fold, compress, or saturate the patch. The patient should follow the product and clinician instructions.
Can iontophoresis dissolve a heel spur?
No. Iontophoresis delivers an ionic medication through the skin. It does not remove bone. Heel spurs are also not considered the primary cause of most plantar-fasciitis pain.
Can iontophoresis heal a torn plantar fascia?
No. A suspected tear requires medical evaluation. Iontophoresis should not be used as a substitute for diagnosis, immobilization, load protection, or another appropriate treatment.
When should the patient be referred?
Refer or obtain medical evaluation when there is trauma, marked swelling, bruising, a suspected stress fracture or fascia tear, neurological symptoms, infection, severe night pain, inability to bear weight, an atypical presentation, or failure to improve with appropriate care.
Related Resources
- Shop iontophoresis patches, electrodes, and dose controllers
- Iontophoresis Treatment Protocol Library
- Iontophoresis Electrode Directions for Use
- Iontophoresis FAQ, Medication, Dose, and Polarity Guides
- ActivaDose II Iontophoresis Controller
- Trivarion Form-Fitting Iontophoresis Electrodes
- Ionto4 Iontophoresis Electrode Kits
- Buffered Iontophoresis Electrode Kits
- IontoPatch Wearable Iontophoresis Patches
- ACTIVApatch Wearable Iontophoresis Patches
- Heel Lifts and Inserts
- Exercise Resistance Bands
- Reusable Hot and Cold Therapy Products
This protocol is intended for professional education. Medication iontophoresis should be performed only under appropriate medical direction and according to the medication labeling, device instructions, electrode instructions, facility policy, and applicable scope-of-practice requirements.


